
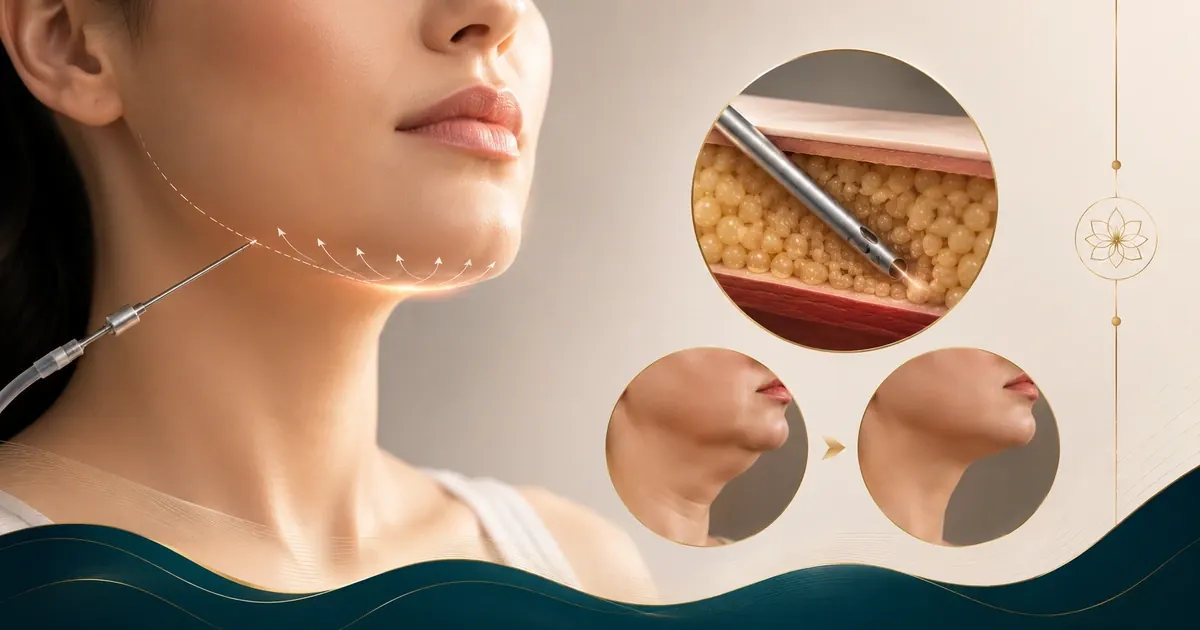
What Chin and Neck Liposuction Actually Treats
Chin and neck liposuction — technically called submental liposuction — targets the fat deposits beneath the chin and along the upper neck that create the appearance of a double chin or a soft, undefined jawline. This is one of the most commonly inherited areas of localised fat. Many patients who are otherwise lean carry disproportionate fat here that is resistant to diet and exercise, as published neck contouring research confirms.2 The procedure can address the submental area alone or extend to the full lateral neck, depending on the patient's anatomy.
Submental Fat (the "Double Chin")
The submental area is the triangular zone directly under the chin, bounded by the lower edge of the mandible above and the hyoid bone below. Submental simply means "beneath the chin" — when surgeons say "submental fat," they mean the fat pad that creates the double chin. This deposit is largely genetic; twin studies and clinical observation consistently show that its size and prominence are partly heritable, independent of overall body weight.
Submental liposuction targets this deposit with a single small incision placed in the natural crease beneath the chin, where the scar is essentially invisible once healed. A thin cannula (2–3 mm) is passed in a fan pattern through the subcutaneous fat layer, aspirating fat evenly. Removing even 40–80 mL of fat from this anatomical position can produce a substantially more defined profile — a small volume with an outsized visual effect because of the jawline's prominence in facial proportion.
Lateral Neck and Pre-Jowl Fat
Beyond the submental triangle, fat can accumulate along the lateral neck and in the pre-jowl sulcus — the area along the lower jaw toward the ear. These deposits soften the jawline, reduce mandibular definition, and create the appearance of jowling even in patients who are not significantly overweight.
Treating lateral neck fat requires additional access incisions placed behind each ear (the post-auricular sulcus) — an inconspicuous location hidden in the ear fold. The cannula is passed forward through these incisions to treat the lateral neck fat and along the lower jawline. Treating the full neck alongside the submental area typically adds 15–30 minutes to operating time but produces a significantly more defined lower facial frame for appropriate candidates.2
What It Cannot Treat: Skin Laxity, Platysmal Banding, Subplatysmal Fat
Understanding the limitations of chin and neck liposuction is just as important as understanding what it achieves. Three specific structures are beyond the scope of liposuction and are the most common reasons patients do not get their expected result when these components are not addressed:
- Skin laxity and excess skin. Liposuction removes volume. If the skin does not retract after fat removal — because elasticity is poor — the result is loose, draped skin rather than a tighter profile. This is addressed surgically by cervicoplasty (skin excision), not by liposuction alone.
- Platysma muscle banding. Vertical cords in the neck are caused by separated or ptotic edges of the platysma muscle, not by fat. These bands are visible at rest and become more pronounced when the jaw is clenched. Liposuction cannot tighten or reposition muscle. Platysmaplasty (surgical plication or transection of the platysma) is required — and removing the fat that was partially concealing bands can actually make them more visible.
- Subplatysmal fat. A proportion of neck fat lies beneath the platysma muscle, between the muscle and the deeper neck structures. This fat is not accessible to surface liposuction without traversing the muscle layer, which significantly increases surgical risk. Subplatysmal fat is addressed during a formal neck lift with open dissection, not by standard liposuction.
A comprehensive neck contouring consultation should assess all three — subcutaneous fat, skin quality, and platysma anatomy — to determine which components are driving the aesthetic concern and which procedure or combination of procedures will address them.2
Are You a Candidate? The Skin Elasticity Test
Chin and neck liposuction candidacy is determined by one central question: is the fullness primarily caused by fat, or does significant skin laxity or muscle laxity also play a role? Getting this assessment right before surgery is the most important determinant of a satisfying outcome.
The Manual Lift Test
The most reliable bedside candidacy test is simple. Stand in front of a mirror and do the following:
- Pinch the skin beneath your chin between thumb and forefinger — gauge how much tissue lifts and whether it feels like fat (soft, compressible) versus loose skin (thin, pliable without much substance).
- Release the pinch and watch how quickly the skin snaps back. Good elasticity means the skin rebounds immediately with minimal residual wrinkling. Poor elasticity means the skin sags back slowly, leaving creases or a drape.
- Place your fingers under your jawline and manually lift the neck skin upward. If this manoeuvre dramatically improves your profile, it suggests the skin itself needs tightening — not just fat removal. That improvement comes from a neck lift, not liposuction alone.
Surgeons perform a clinical version of this test at consultation. The snap-back speed tells them how much collagen and elastin remain in the dermis. Patients with good recoil are the strongest liposuction candidates; those whose skin drapes or hangs independently of the fat volume are better served by a lift.
When a Neck Lift Is the Right Operation Instead
A neck lift (which may encompass cervicoplasty, platysmaplasty, or lower facelift components) is appropriate when skin laxity, platysma banding, or subplatysmal fat are significant contributors. Signs that a neck lift may be more appropriate include:
- The neck skin droops or sags independently of the fat volume — visible even when lying down
- Vertical platysma bands are visible at rest or with any neck movement
- Prior significant weight loss that stretched and loosened the neck skin
- The manual lift test shows dramatic improvement — meaning skin excision or tightening (not just fat removal) will deliver the desired result
- Age-related skin changes have produced diffuse laxity throughout the lower face and neck
Performing liposuction in a patient with significant laxity risks worsening the appearance — removing the fat that was supporting the skin leaves it emptier and more visibly loose.3 A surgeon who does not evaluate skin quality before recommending neck liposuction is a meaningful red flag.
Weight Stability and BMI Considerations
The ideal candidate for chin and neck liposuction shares these characteristics:
- Good skin elasticity — the skin springs back when pinched and released
- Localised subcutaneous fat as the primary concern — pinchable, compressible tissue, not a skin drape or muscle band
- Stable weight. Patients at or near their normal weight range will have the most predictable outcomes. Neck liposuction is a contouring procedure, not a weight-loss procedure. A BMI generally under 30 is recommended, though anatomy matters more than a number
- No significant platysma banding — visible neck cords at rest require surgery, not lipo
- Realistic expectations — a defined cervicomental angle and a cleaner jawline are achievable; complete facial rejuvenation is not
Age alone is not a disqualifying factor — many patients in their 40s and 50s have excellent skin tone and are strong candidates for liposuction without a lift. Conversely, younger patients who have had dramatic weight loss may have poor skin quality despite their age. The elasticity test, not the calendar, determines candidacy.
| Patient profile | Primary concern | Recommended approach |
|---|---|---|
| Submental fat, good skin elasticity, no banding | Localised fat | Submental / neck liposuction alone |
| Fat + mild early skin laxity, age 30–45 | Fat predominant; modest laxity | Neck liposuction; discuss residual laxity risk |
| Fat + visible platysma banding | Fat + muscle | Liposuction + platysmaplasty (open procedure) |
| Moderate fat + significant skin laxity | Fat + laxity | Combined neck liposuction + cervicoplasty |
| Significant laxity, banding, subplatysmal fat, age 55+ | Multi-component aging | Formal neck lift; liposuction as adjunct only |
How the Procedure Works
Chin and neck liposuction follows the same fundamental principles as liposuction elsewhere — tumescent fluid infiltration, fat aspiration via cannula, and compression during healing — but the anatomy of the neck demands particular attention to even fat removal and cannula depth, because the neck skin is thin and irregularities show readily.5
Marking and Tumescent Infiltration
On the day of surgery, the surgeon marks the treatment zones with the patient upright — gravity-dependent fat distribution in the neck makes upright marking essential because fat that bulges while seated may redistribute when lying flat. Markings typically delineate the central submental fat triangle, the lateral extent toward each jowl, the inferior boundary (usually the level of the hyoid bone), and the planned incision sites.
Tumescent anaesthesia is the standard preparation. A dilute lidocaine and epinephrine solution in saline is infiltrated into the subcutaneous fat. Epinephrine narrows blood vessels and reduces bleeding. Lidocaine numbs the area for several hours. This page does not quote the drug concentrations.
A pivotal series of 695 consecutive submental liposuction cases performed under tumescent local anaesthesia confirmed the safety and efficacy of this approach, with very low complication rates and high patient satisfaction.1
Incision Placement and Why Scars Are Usually Hidden
Neck liposuction requires two or three small access incisions, each approximately 3–4 mm:
- Submental crease incision: A single stab incision within the natural skin crease directly below the chin. This is the primary access point for the submental fat triangle — the scar in this location is virtually undetectable once healed.
- Post-auricular incisions: One incision behind each ear, placed within the natural skin fold where the ear meets the jaw skin. These provide lateral access for treating jowl fat and the lateral neck. They are only required when treatment extends beyond the submental triangle.
The incisions are small enough that they do not require sutures at initial closure — they are left slightly patent to allow residual tumescent fluid to drain during the first 12–24 hours, which reduces bruising and swelling. A single absorbable stitch or skin tape is applied once drainage is complete. By 3–6 months, the incision sites are nearly invisible in most patients and not noticeable with normal neck positioning.
Volume: Why 40–80 mL Changes a Profile
The cannula used for neck liposuction is typically 2–3 mm outer diameter — smaller than those used for body areas. The surgeon passes it in a radial fan pattern from each incision, aspirating fat in even, parallel strokes while continuously pinching the skin to assess remaining fat thickness and ensure even removal.
Total aspirate volume for chin and neck liposuction is typically 40–80 mL — modest by any measure, and dramatically less than the 500–5,000 mL removed from body areas. But this small volume produces a highly visible result because of where the fat sits: the submental area is the most visible fat deposit on the face, directly framing the jawline and neck profile. Removing 40–80 mL from this position creates a substantially sharper cervicomental angle (the angle between the underside of the chin and the front of the neck) — the angle most associated with a lean, defined profile.
At closure, remaining tumescent fluid is expressed, incisions are taped, and a compression chin strap is applied before the patient leaves the operating room. Total procedure time: 30–90 minutes depending on whether treatment covers chin only or the full neck and jowl zone. Most patients are discharged within 1–2 hours.
Anaesthesia Options
Chin and neck liposuction has a significant advantage over larger body liposuction: it can almost always be performed under local anaesthesia alone. The 695-case series under local anaesthesia confirmed this is safe and sufficient for the majority of patients.1 Three options exist:
| Type | Best suited for | Cost impact |
|---|---|---|
| Local tumescent only | Isolated submental / neck; most patients | Lowest — no anaesthetist |
| IV sedation (twilight) | Full neck + jowl; anxious patients | Moderate — adds $500–$1,200 for the sedation itself. Treating the full neck and jowl zone is quoted at $3,500–$7,000 in the US, about $1,000–$1,500 more than a chin-only quote |
| General anaesthesia | Combined procedures (neck lift, facelift) | Highest — adds $1,000–$2,500 |
Most patients tolerate local anaesthesia well. The initial tumescent injections cause brief stinging; once the lidocaine takes effect, patients feel pressure and vibration from the cannula but not pain. Recovery from local is immediate — patients walk out of the clinic after a short observation. General anaesthesia is rarely justified for chin and neck liposuction alone.
Recovery Week by Week
Chin and neck liposuction has one of the most forgiving recovery profiles among liposuction areas. The treatment zone is small, incisions are tiny, and the procedure is typically performed under local anaesthesia — meaning patients are alert and comfortable within an hour of finishing.
First 72 Hours
The first three days are the most uncomfortable. Patients experience:
- Swelling: The neck and submental area will appear larger immediately after surgery than before, owing to tumescent fluid redistribution and surgical oedema. This peaks at 24–48 hours.
- Bruising: Ecchymosis typically appears across the neck and submental area by day two. Epinephrine in the tumescent solution reduces but does not eliminate bruising.
- Tightness: The neck feels tight and stiff — partly from the compression garment, partly from oedema.
- Fluid drainage: Pinkish watery fluid may drain from incision sites for 12–36 hours. This is normal and desirable — it reduces bruising by allowing residual tumescent fluid to exit.
Pain is typically mild to moderate — patients describe it as a tight sunburn rather than acute pain. Oral analgesics (paracetamol / ibuprofen) are sufficient. The chin strap compression garment is worn 24/7 during this phase.
Weeks 1–2
Most patients return to desk work by day 5–7. Visible bruising — which typically extends from the submental area across the lower neck — peaks in colour during days 3–7, then begins to yellow and fade during week two. By the end of week two, most patients see the first glimpse of their improved profile as swelling lifts from the submental area.
Activity restrictions: no strenuous exercise or heavy lifting; sleep with the head elevated 30–45 degrees (wedge pillow or recliner) to reduce overnight oedema. The compression garment is worn 24 hours, removed only for showering. Light walking is encouraged from day one.
Weeks 3–6
By week three, most social activities are comfortable. Residual bruising is usually gone. The compression garment transitions to night-only wear around weeks 3–4. Light aerobic exercise (walking, cycling) typically resumes at week three; higher-impact activities (running, weights) are cleared at weeks four to six.
A common experience in this phase is intermittent tightness or areas of hardness under the skin. This is normal post-liposuction fibrosis — scar tissue forming in the treated fat layer — and resolves with time and gentle massage. Lymphatic drainage massage starting around week two helps soften the tissue and accelerate oedema resolution.
When Swelling Really Settles
The result seen at six weeks is usually a reasonable preview of the final outcome, but the last stages of swelling continue to resolve through months three to four. Deeper firmness — a subtle stiffness that patients can feel but others typically cannot see — may persist until month four to six. The final contour, with all oedema resolved and skin fully retracted, is typically stable at 3–4 months.
The Chin Compression Garment: What It Does and Doesn't Do
The compression chin strap serves three purposes: it reduces oedema accumulation, supports the skin as it conforms to the new contour, and applies gentle counterpressure to the treated area. It is worn continuously for the first week (24/7), then at night only for weeks 2–3. After that, most surgeons discontinue it.
What it does not do: it does not "shrink" fat, accelerate fat removal, or tighten loose skin. If the skin does not have adequate elasticity to retract after fat removal, a compression garment will not compensate. It is a recovery aid, not a corrective device.
| Timeframe | What to expect | Activity level |
|---|---|---|
| Day 1–3 | Peak swelling; bruising developing; tightness; fluid drainage; compression 24 hrs | Rest; light walking only |
| Days 3–7 | Bruising at peak colour; swelling starts to ease; mild soreness | Desk work from day 5–7; avoid exertion |
| Week 2 | Bruising fading to yellow; first signs of improved profile; incisions healing | Full desk work; light daily activities |
| Weeks 3–4 | Bruising resolved; garment to nights only; may feel firmness under skin | Light exercise resumes |
| Weeks 4–6 | Social activities comfortable; gradual swelling reduction continues | Full exercise cleared at week 4–6 |
| Months 3–4 | Final result; all oedema resolved; contour stable; skin fully retracted | Unrestricted |
Results: What Changes, What Doesn't, How Long It Lasts
Chin and neck liposuction, when performed in correctly selected patients, produces some of the most visually impactful results per volume of fat removed of any liposuction area. A sharper cervicomental angle, a defined jawline, and a leaner lower facial profile are the hallmarks of a successful outcome.
Why Removed Fat Cells Don't Come Back — and Why Weight Gain Still Changes the Result
The fat cells removed by liposuction are permanently gone — adipocytes do not regenerate after adulthood.5 This means the structural improvement to the cervicomental angle and neck profile is lasting as long as body weight remains stable.
If weight rises a lot after surgery, the fat cells that remain, including any left in the neck, enlarge. The contour then looks less sharp. The treated area has fewer fat cells than it did, so it usually stores less of a new gain than an untreated area. This page does not define that gain as a percentage of body weight.
Patients who maintain stable weight after chin and neck liposuction typically enjoy their results for many years. The progressive aging changes that occur with time — gradual skin laxity, platysma changes — are independent of the liposuction and may lead patients to consider a neck lift in later years as age-related changes accumulate.
What Before-and-After Photos Can't Show You
Before-and-after photographs are useful but inherently limited. They show a visual improvement in jawline definition and submental fullness, but they cannot convey:
- How the skin feels. After liposuction, the treated area may feel firm, numb, or slightly uneven for weeks to months as fibrosis forms and resolves. This tactile experience is invisible in photographs.
- Lighting and angle bias. Professional before-and-after photos are taken in controlled lighting that can exaggerate or minimise results. Real-world lighting (video calls, candid side-on shots) is less flattering and more representative of what others see.
- Swelling timeline. Many "after" photos are taken at 3–6 months, when swelling is fully resolved. Photos taken at 2–4 weeks may look less impressive due to residual oedema.
- What liposuction could not fix. Residual skin laxity, platysma bands, or a low hyoid bone position are not visible in standard before-and-after photography but may be apparent in person or in motion.
Ask to see photos of patients with a similar starting anatomy and skin quality to yours — not the surgeon's best-case result on a 25-year-old with perfect elasticity.
Is chin and neck liposuction worth it?
It is worth considering when the fullness under the chin is pinchable fat, the skin snaps back in the mirror test above, and your weight is stable. It is the wrong operation when the change you see comes from loose skin or muscle bands, or when the goal is weight loss. If lifting the skin with your fingers changes the profile more than pinching the fat does, a neck lift matches the problem and liposuction does not.
A published review of injectable deoxycholic acid for submental fat contouring found it can reduce a small fat pocket, but it takes several sessions and the result is less predictable than liposuction when the deposit is larger.4
| Chin and neck liposuction | Deoxycholic acid injections | |
|---|---|---|
| US price | $2,500–$5,500, one operation | $2,400–$7,200 for a course of 2–4 sessions ($1,200–$1,800 per session) |
What chin alone costs versus chin plus neck, and how countries compare, is on the chin liposuction cost page.
Risks and What Can Go Wrong
Submental liposuction is among the lowest-risk liposuction procedures — the area is small, the procedure is short, and it is routinely performed under local anaesthesia. The 695-case series reported a low complication rate when performed by experienced surgeons.1 Still, no surgical procedure is without risk:
| Complication | Frequency | Management |
|---|---|---|
| Bruising and swelling | Expected (virtually all patients) | Resolves spontaneously in 1–4 weeks |
| Temporary numbness | Common | Resolves within 6–12 weeks; no treatment required |
| Contour irregularity | Uncommon | Observation for 3 months; minor touch-up if persistent |
| Hypertrophic scarring | Uncommon; higher in predisposed individuals | Silicone gel, steroid injection, or laser |
| Infection | Rare | Antibiotics; drainage if abscess forms |
| Marginal mandibular nerve injury | Rare in experienced hands | Usually temporary; permanent injury very rare |
| Haematoma | Rare | Aspiration or drainage depending on size |
The marginal mandibular nerve — the branch of the facial nerve controlling lower lip movement — is the most important anatomical risk specific to this region. It runs superior to the typical cannula plane in submental liposuction, making injury rare in experienced hands. For a broader overview of liposuction safety, see our when liposuction goes wrong guide.
What It Costs
Chin and neck liposuction is the least expensive liposuction area due to the small treatment zone, short operating time, and local anaesthesia eligibility — US total costs run $2,500–$5,500; Turkey all-inclusive packages average $800–$1,800. Our chin and neck liposuction cost breakdown covers country-by-country pricing, what affects the price, the cost comparison with deoxycholic acid injections, and what's included in each quote.
Frequently Asked Questions
-
For patients with isolated submental fat and good skin elasticity, chin liposuction offers a one-time contour change with a few days of downtime. Whether it is worth it depends on the mirror test in the section above, not on the fee. The price comparison with deoxycholic acid injections is in that same section, and the full quote is on the chin liposuction cost page.
-
Results are permanent in the sense that removed fat cells do not come back. A large weight gain can enlarge the fat cells that remain, including in the neck, and the contour looks less sharp. People who keep a stable weight keep the change. Age-related skin changes are a separate process.
-
No — submental liposuction is one of the lowest-risk liposuction procedures. The area is small, the procedure is short, and it is typically performed under local anaesthesia. A 695-case series under local anaesthesia reported minimal complications.1 Serious complications such as nerve injury or infection are uncommon in experienced hands. The most common side effects are temporary bruising, swelling, and numbness.
-
Usually not. Most chin and neck liposuction is performed under local tumescent anaesthesia alone — no sedation or general anaesthesia required. IV sedation is an option for anxious patients. General anaesthesia is reserved for combined procedures such as a simultaneous neck lift or facelift.
-
The 2–3 incisions are approximately 3 mm each, placed in natural skin creases under the chin and behind the earlobes. They heal to nearly invisible marks within 3–6 months. Patients prone to keloid scarring or darker skin tones should discuss hyperpigmentation risk with their surgeon.